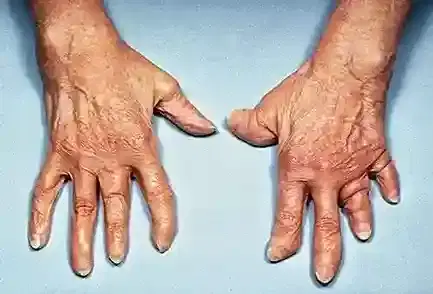
Psoriatic Arthritis
5K+ International Patients Treated
40+ Source Countries Served
500+ Accredited Partner Hospitals
98% Patient Satisfaction
80% Average Savings vs USA
10K+ Doctors
NABH, JCI Accredited Hospitals
Free Treatment Plan
Free Consultation with Doctor
5+ Destinations Covered
About Psoriatic Arthritis
Sources and Guidelines Referenced
The following clinical guidelines and landmark research studies form the evidence base for this document: EULAR Recommendations for Management of Psoriatic Arthritis (Gossec et al., 2020/2023 update); GRAPPA Treatment Recommendations for Psoriatic Arthritis (Coates et al., 2021); ACR/NPF Guideline for the Treatment of Psoriatic Arthritis (Singh et al., 2018); European Academy of Dermatology and Venereology (EADV) Guidelines (2021); Tight Control in Psoriatic Arthritis (TICOPA) Trial (Coates et al., 2015); SPIRIT Clinical Trial Program (Mease et al., 2020); FUTURE Clinical Trial Program (McInnes et al., 2019).
Psoriatic Arthritis: A Comprehensive Patient Guide
1. Definition and Medical Identity
Psoriatic arthritis is a chronic, autoimmune inflammatory condition affecting the musculoskeletal system and skin. It occurs when immune dysregulation leads to joint swelling, skin lesions, and entheseal tissue breakdown. Managed primarily within rheumatology, the fundamental clinical goal is halting joint damage and achieving systemic remission.
The condition belongs to the seronegative spondyloarthropathy disease family, meaning affected individuals typically test negative for rheumatoid factor in blood panels. The disease exhibits heterogeneous presentation, meaning symptoms vary significantly among individuals. Medical literature categorizes psoriatic arthritis into peripheral patterns (affecting hands, feet, wrists, knees, and ankles) and axial patterns (affecting the spine and sacroiliac joints). Advanced disease management relies on targeted immunomodulatory agents to regulate pathogenic biochemical cascades.
2. The Underlying Condition or Need
Psoriatic arthritis develops from complex interactions between underlying genetic markers and environmental triggers. Immune dysfunction causes systemic cellular activation, leading to sustained tissue inflammation, joint breakdown, and soft tissue swelling.
Patients present with joint stiffness lasting longer than 30 minutes in the morning, visible joint swelling, localized heel or tendon pain, and scaly skin plaques. Left untreated, chronic inflammation causes cartilage breakdown, bone erosions, and joint deformity. Persistent inflammatory activity also increases long-term risk for cardiovascular disease, metabolic syndrome, and metabolic bone loss (EULAR, 2023). Early therapeutic intervention prevents structural architecture collapse and permanent physical disability.
3. How the Treatment Works — Mechanism
Psoriatic arthritis management works by interrupting specific molecular pathways that drive cellular inflammation. Advanced therapeutic agents target pro-inflammatory signaling proteins, stopping the autoimmune inflammatory cascade at the cellular level.
Biologic and targeted medications focus on key inflammatory mediators: tumor necrosis factor (TNF), interleukin-17 (IL-17), and interleukin-23 (IL-23). These signaling molecules normally coordinate host defense against infections; however, in autoimmune disease, their overproduction drives chronic inflammation. Targeted biologic antibodies bind directly to these proteins, neutralizing their activity. Oral targeted synthetic agents inhibit intracellular pathways, such as Janus kinase (JAK) enzymes or phosphodiesterase-4 (PDE4), stopping inflammatory gene transcription inside immune cells (GRAPPA, 2021).
4. Types and Variations
Treatment protocols for psoriatic arthritis encompass five main therapeutic categories. Selection depends on specific individual joint domains, skin severity, and prior therapeutic responses.
| Treatment Category | Primary Mechanism | Targeted Domains | Route of Administration |
|---|---|---|---|
| csDMARDs (e.g., Methotrexate) | Inhibits folate metabolism and cellular proliferation | Peripheral arthritis | Oral or subcutaneous weekly |
| TNF Inhibitors | Neutralizes tumor necrosis factor alpha | Peripheral, axial, enthesitis, dactylitis, skin | Subcutaneous or intravenous |
| IL-17 Inhibitors | Selectively blocks interleukin-17A cytokines | Peripheral, axial, enthesitis, dactylitis, skin | Subcutaneous injection |
| IL-23 Inhibitors | Selectively blocks the p19 subunit of interleukin-23 | Peripheral, enthesitis, dactylitis, severe skin | Subcutaneous injection |
| JAK Inhibitors | Inhibits intracellular Janus kinase signaling pathways | Peripheral, axial, enthesitis, skin | Oral daily medication |
Clinicians evaluate which disease domains are predominant before initiating treatment. For example, patients presenting primarily with axial spine involvement derive limited benefit from conventional synthetic medications like methotrexate, making biologic agents the initial drug of choice (ACR/NPF, 2018).
5. Who the Treatment Is For — Indications
Systemic treatment is indicated for patients with a confirmed diagnosis of active psoriatic arthritis who exhibit persistent joint inflammation, dactylitis, enthesitis, or structural skin lesions. Clinical decision-making relies on objective diagnostic scoring systems.
- Confirmed diagnosis according to the CASPAR criteria (Classification Criteria for Psoriatic Arthritis), requiring inflammatory articular disease alongside psoriasis indicators.
- Active peripheral arthritis involving one or more tender and swollen joints.
- Active enthesitis (such as Achilles tendonitis or plantar fasciitis) causing pain and functional restriction.
- Presence of dactylitis ("sausage digit") unresponsive to local measures.
- Active axial skeleton involvement with objective inflammatory back pain features.
- Elevated inflammatory markers, including C-reactive protein (CRP) or erythrocyte sedimentation rate (ESR), supported by ultrasound or MRI evidence of active inflammation.
6. Who the Treatment Is NOT For — Contraindications
Therapeutic agents used in psoriatic arthritis are contraindicated in patients with severe active systemic infections, untreated latent tuberculosis, or unmanaged organ failure. Specific agent classes require distinct clinical exclusions.
Absolute contraindications include severe systemic sepsis, active tuberculosis infection, hepatitis B virus reactivation risk without antiviral coverage, and known hypersensitivity to specific drug components. Relative contraindications require modification of protocol: TNF inhibitors are contraindicated in patients with moderate-to-severe congestive heart failure (NYHA Class III/IV) and demyelinating disorders such as multiple sclerosis (Singh et al., 2018). Patients with a history of recurrent mucosal fungal infections require cautious evaluation before starting interleukin-17 inhibitors. Live vaccines are strictly prohibited during biological treatment.
7. Alternatives and Clinical Comparison
Management alternatives range from topical agents and symptomatic anti-inflammatory drugs to targeted biological and oral synthetic agents. Selecting appropriate options depends on disease severity, structural involvement, and treatment safety profiles.
| Therapy Class | Mechanism | Invasiveness | Monitoring Requirements | Clinical Trade-offs |
|---|---|---|---|---|
| NSAIDs | Symptom reduction via COX inhibition | Non-invasive (Oral) | Minimal blood/renal panels | Relieves pain; does not prevent joint damage |
| csDMARDs | Broad immune suppression | Non-invasive (Oral/SQ) | Frequent CBC, liver enzyme panels | Lower expense; modest efficacy for spine/enthesitis |
| bDMARDs | Targeted cytokine blockade | Minimally invasive (Injections) | Pre-screening for infection, basic labs | High clinical efficacy; requires parenteral administration |
| tsDMARDs | Targeted intracellular enzyme blockade | Non-invasive (Oral) | CBC, lipid panels, liver tests | Oral convenience; specific infection/cardiovascular risks |
Symptomatic therapies like NSAIDs do not alter the disease trajectory. Disease-modifying antirheumatic drugs (DMARDs) are necessary to stop structural bone erosions and preserve physical function (Coates et al., 2021).
8. Pre-Treatment Phase
The pre-treatment phase focuses on comprehensive diagnostic validation, safety screening, infection prevention, and clinical baseline measurements. Detailed laboratory evaluations ensure safe therapeutic administration.
During initial consultation, rheumatologists perform a physical exam evaluating 66 swollen and 68 tender joint counts. Diagnostic screening includes blood testing for rheumatoid factor and anti-cyclic citrullinated peptide to rule out rheumatoid arthritis. Screening for latent tuberculosis using an interferon-gamma release assay, along with hepatitis B and C screening, is required before initiating targeted therapies (Gossec et al., 2020). Patients must receive recommended non-live vaccines—including pneumococcal, influenza, and shingles vaccines—at least two to four weeks before starting immunosuppressive regimens.
9. The Procedure — Step-by-Step Clinical Detail
Psoriatic arthritis management follows a standardized, continuous outpatient medical administration protocol. Treatment transitions through distinct clinical steps to achieve target outcomes.
Phase 1: Diagnostic and Baseline Evaluation
The clinical team establishes baseline joint counts, complete skin assessment scores, and functional impairment levels. Baseline imaging via plain radiography or musculoskeletal ultrasound records current bone structures and soft tissue swelling.
Phase 2: Therapeutic Initiation and Induction
Depending on the prescribed medication, treatment starts with oral administration, subcutaneous self-injection, or intravenous infusion. Oral medications are taken daily or weekly. Certain biologic medications require loading doses given at weeks 0, 1, 2, and 4 to establish steady blood concentrations.
Phase 3: Outpatient Infusion or Self-Injection Maintenance
Subcutaneous injections are administered by the patient at home every one to four weeks using auto-injector devices. Intravenous biologic treatments are administered in an outpatient clinic over 30 to 120 minutes with regular vital sign monitoring.
Phase 4: Safety Assessment and Response Monitoring
Patients undergo lab evaluations at four- to twelve-week intervals to monitor liver enzymes, full blood counts, and kidney performance. Medical evaluations track joint index scores to confirm clinical efficacy.
10. Immediate Post-Procedure Period
Following initial self-injections or outpatient infusions, immediate clinical priority focuses on tracking adverse reactions and injection site responses. Patients receive detailed instructions on observing symptoms.
For intravenous infusions, post-procedure observation lasts 30 to 60 minutes to manage potential hypersensitivity reactions like rash, fever, or dizziness. Mild subcutaneous injection site reactions—such as localized redness, minor swelling, or itching—occur in up to 10 percent of patients and typically resolve within 48 hours without intervention. Patients are advised to maintain fluid hydration and report early signs of localized or systemic infection immediately.
11. Recovery — Short and Long Term
In chronic disease management, "recovery" refers to controlled disease activity and symptom remission. The timeline for achieving therapeutic response varies across medication classes.
Symptom improvement with conventional drugs like methotrexate takes 8 to 12 weeks. Biologic therapies targeting TNF, IL-17, or IL-23 pathways often show visible joint relief and reduced morning stiffness within 2 to 4 weeks, with maximal benefits achieved at 16 to 24 weeks (McInnes et al., 2019). The primary long-term management goal is sustaining minimal disease activity (MDA), defined as meeting specific targets across joint counts, skin scores, pain scales, and enthesitis measures. Regular follow-up every 3 to 6 months ensures early identification of treatment failure or disease flare-ups.
12. Risks, Side Effects, and Complications
Pharmacological therapies for psoriatic arthritis carry distinct side effect profiles related to immune pathway modulation. Risks range from self-limiting local symptoms to severe systemic adverse events.
| Severity Level | Possible Side Effects / Complications | Clinical Action / Management |
|---|---|---|
| Mild / Common | Injection site reactions, transient nausea, mild upper respiratory tract viral infection | Symptomatic care, cold compresses, dosage adjustment | 特
| Moderate / Uncommon | Elevated hepatic enzymes, mild cytopenias, cutaneous fungal (Candida) infections | Routine laboratory monitoring, topical anti-fungal treatment |
| Severe / Rare | Serious systemic bacterial/fungal infections, latent tuberculosis reactivation, demyelination, opportunistic infections | Immediate drug cessation, intravenous antibiotics, targeted specialist management |
Long-term safety registries demonstrate that targeted biological therapies carry a small increase in serious infection risk compared to the general population. Proper pre-treatment screening and regular lab monitoring significantly reduce these risks (Singh et al., 2018).
13. Lifestyle and Behavioural Considerations
Lifestyle interventions support medical management by reducing systemic background inflammation, mitigating mechanical joint strain, and addressing cardiovascular risks. Behavioral changes complement disease-modifying therapies.
Obesity increases joint strain and promotes systemic low-grade inflammation, which can reduce the therapeutic efficacy of anti-TNF agents (Coates et al., 2021). Weight loss programs and low-impact cardiovascular exercise (such as swimming, cycling, and walking) reduce mechanical strain, preserve muscle strength, and protect joint flexibility. Smoking cessation is essential, as tobacco use is associated with reduced response to biologic treatments and increased disease activity. Balanced anti-inflammatory diets, such as the Mediterranean diet, help manage co-existing cardiovascular risks.
14. How Outcomes Are Measured
Clinical success in psoriatic arthritis management is measured using validated composite assessment tools and longitudinal imaging studies. Evaluations track both subjective symptom relief and objective structural protection.
Rheumatologists measure clinical response using standardized composite indexes, including the Disease Activity Index for Psoriatic Arthritis (DAPSA) and Minimal Disease Activity (MDA) criteria. MDA achievement requires meeting at least 5 of 7 specific clinical targets, such as a tender joint count of 1 or fewer and a psoriasis skin surface area of 3 percent or less. Radiographic outcomes are assessed using standardized scoring systems (e.g., modified Sharp-van der Heijde score) every 1 to 2 years to verify the absence of structural joint breakdown (Gossec et al., 2020).
15. Recent Advances and Current Standard of Care
Psoriatic arthritis treatment has advanced considerably with targeted biologic discovery and structured therapeutic protocols. Early intervention within a "window of opportunity" helps preserve long-term joint health.
The current standard of care uses a treat-to-target approach. The landmark TICOPA trial established that frequent disease monitoring and prompt treatment escalation lead to significantly better clinical outcomes than standard care (Coates et al., 2015). Recent pharmacological advancements include selective IL-23 p19 inhibitors and oral JAK inhibitors, which offer target-specific options for patients with inadequate responses to traditional anti-TNF therapies. Musculoskeletal ultrasound at the bedside allows immediate visualization of enthesitis and subclinical synovitis, enabling timely treatment adjustments.
16. Common Myths and Misconceptions
Misconceptions regarding psoriatic arthritis often cause delays in seeking appropriate specialty care. Addressing these myths helps patients make informed, evidence-based management decisions.
Myth: Psoriatic arthritis is simply skin psoriasis with minor age-related joint soreness.
Reality: Psoriatic arthritis is an aggressive autoimmune joint condition capable of causing rapid, permanent joint destruction and structural deformity without targeted systemic therapy (EULAR, 2023).
Myth: Joint damage from psoriatic arthritis can be fully reversed once systemic treatment begins.
Reality: Current systemic treatments suppress active joint inflammation and halt progression, but they cannot reverse established structural bone erosions, emphasizing the critical importance of early treatment.
Myth: Dietary changes alone can cure psoriatic arthritis and replace immune-modifying medications.
Reality: While healthy dietary habits support cardiovascular health, high-level clinical trial evidence shows dietary changes alone cannot arrest underlying autoimmune joint destruction (Coates et al., 2021).
Myth: Biologic medications cause permanent suppression of the entire immune system.
Reality: Modern targeted biologics block specific inflammatory cytokines rather than causing generalized immune breakdown, allowing selective immune protection against common pathogens.
Myth: Absence of elevated rheumatoid factor in blood tests rules out inflammatory joint disease.
Reality: Psoriatic arthritis is classified as a seronegative spondyloarthropathy; over 80 percent of patients test negative for rheumatoid factor despite active joint inflammation.
Myth: Pain management with over-the-counter NSAIDs is sufficient to control psoriatic arthritis.
Reality: NSAIDs temporarily relieve symptoms but do not stop underlying cartilage damage, bone erosions, or long-term disability.
17. Frequently Asked Questions
What is psoriatic arthritis?
Psoriatic arthritis is an autoimmune condition causing joint swelling, tendon inflammation, and skin plaques. It occurs when immune dysregulation leads to tissue breakdown in joints, entheses, and skin structures.
How does psoriatic arthritis differ from rheumatoid arthritis?
Psoriatic arthritis often involves asymmetric joint distribution, dactylitis, enthesitis, spinal involvement, and negative rheumatoid factor testing, whereas rheumatoid arthritis typically presents with symmetric small joint swelling and positive autoantibody markers.
What is enthesitis in psoriatic arthritis?
Enthesitis is inflammation at the sites where tendons or ligaments attach to bone. Common locations include the Achilles tendon and plantar fascia, causing localized pain, swelling, and reduced mobility.
Can psoriatic arthritis occur without visible skin psoriasis?
Yes. Approximately 10 to 15 percent of patients develop joint inflammation before skin lesions appear. A family history of psoriasis provides critical diagnostic evidence in these clinical scenarios.
How long does it take for biologic therapies to show results?
Symptom improvement typically begins within two to four weeks of starting biologic therapy. Maximum clinical joint improvement and skin clearing are usually achieved between 16 and 24 weeks of consistent administration.
What laboratory tests monitor treatment safety?
Routine safety monitoring requires complete blood counts, hepatic enzyme evaluations, and kidney function panels performed every 8 to 12 weeks to monitor for potential adverse effects.
Are biological injections for psoriatic arthritis painful?
Subcutaneous injections using modern auto-injector pens cause minimal discomfort. Allowing the room-temperature medication to settle for 30 minutes prior to injection reduces localized stinging.
Does psoriatic arthritis cause permanent joint damage?
Without targeted systemic treatment, persistent synovial inflammation causes irreversible cartilage loss and bone erosion. Early intervention with disease-modifying agents prevents permanent joint structure collapse.
Is exercise safe for individuals with active psoriatic arthritis?
Yes. Low-impact exercise, such as swimming, cycling, and targeted physical therapy, helps maintain range of motion and joint stability without exacerbating active inflammation.
Can psoriatic arthritis affect the spine?
Yes. Axial involvement causes inflammatory back pain, stiffness, and reduced spinal mobility. Biologic agents specifically targeting TNF or IL-17 pathways treat axial disease effectively.
What happens if an individual stops taking their medication?
Discontinuing disease-modifying therapies usually results in recurrence of joint inflammation, skin flares, and progressive bone erosion. Treatment adjustments should always be managed by a rheumatologist.
Why is tuberculosis screening required before starting biological therapy?
Biologic medications modulate cytokine signaling pathways required to contain latent tuberculosis infections. Screening ensures latent tuberculosis is identified and treated before immunosuppressive therapy begins.
Booking With DIVINHEAL
Get a free consultation to understand your treatment options
Cost Calculator
I know my treatment — show me cost from 3 hospitals
Plan My Journey
Tell us your condition and budget — our AI matches the right destination, hospital and doctor and visa pathway
Recommended Article

Best In Vitro Fertilization (IVF) Doctors in Hyderabad
Doctors for Nephrology: Find Kidney Care Specialists
Doctors in Chennai: Find Medical Specialists in India
Best Embryo Freezing Hospitals in Hyderabad: Care Guide
Hospitals for reproductive surgery: Compare options
Hospitals in Gurugram: Guide to Quality Facilities
IVF Treatment in Haryana | Cost, Hospitals & Doctors
TAVR (Transcatheter Aortic Valve Replacement) cost in New Delhi
Tonsillectomy & Adenoidectomy Success Rate in Mumbai
Facelift & Anti-Aging Procedures in Chennai for Ethiopia Patients | Cost, Hospitals
Booking With DIVINHEAL
Get a free consultation to understand your treatment options
Cost Calculator
I know my treatment — show me cost from 3 hospitals
Plan My Journey
Tell us your condition and budget — our AI matches the right destination, hospital and doctor and visa pathway
Recommended Article
Best In Vitro Fertilization (IVF) Doctors in Hyderabad
Doctors for Nephrology: Find Kidney Care Specialists
Doctors in Chennai: Find Medical Specialists in India
Best Embryo Freezing Hospitals in Hyderabad: Care Guide
Hospitals for reproductive surgery: Compare options
Hospitals in Gurugram: Guide to Quality Facilities
IVF Treatment in Haryana | Cost, Hospitals & Doctors
TAVR (Transcatheter Aortic Valve Replacement) cost in New Delhi
Tonsillectomy & Adenoidectomy Success Rate in Mumbai
Facelift & Anti-Aging Procedures in Chennai for Ethiopia Patients | Cost, Hospitals
Our Speciality and Treatments
Genetic Disorder Diagnosis & Counselling
Pediatric Laparoscopic Surgery
Pediatric Kidney Transplant
Pediatric Cardiac Surgery
Down Syndrome Comprehensive Care
Vaccination Program
Newborn Care Package
Pediatric Intensive Care (PICU)
Pediatric Urology (incl. Hypospadias)
Pediatric Orthopedics
Pediatric Gastroenterology
Pediatric Pulmonology
Pediatric Endocrinology
Pediatric Cardiology (non-surgical)
Pediatric Oncology
Neonatal Intensive Care (NICU)
pediatric neurosurgery






Meet Our Medical Specialists




Sr. Consultant - Urology & Kidney Transplant Program (Unit I)
Dr. Abhinandan Mukhopadhyay
MBBS, MD
India

Sr. Consultant - Urology & Kidney Transplant Program (Unit I)
Dr. Abhinandan Mukhopadhyay
MBBS, MD
India
Hospitals
NABH & JCI Accredited Hospitals in India,Turkey, Thailand & UAE.

Artemis Hospital
Sector 51, Gurugram, Haryana, India

Lokmanya Hospitals
Not Specified

White Lotus Hospital
766, SFS 3145, SFS Road, 7th Sector, HSR Layout, Bengaluru, Karnataka 560102, India

Institute of Brain and Spine (IBS Hospital)
Not Specified
How DivinHeal Helps
We simplify your medical journey by providing comprehensive support and access to world-class healthcare.
Expert Specialist Matching
Connecting you with the world's top-rated medical experts.
Accredited Hospital Network
Access to JCI & NABH certified healthcare facilities.
Complete Travel Coordination
Hassle-free visa, stay, and local transport assistance.
24/7 Personal Care
Dedicated patient advisors supporting you at every step.
Journey Guidance
Full guidance from start to end of the patient treatment journey.
Expert Specialist Matching
Connecting you with the world's top-rated medical experts.
Everything you
need to know today
Browse through these common inquiries to better understand our patient-focused medical platform.
Yes, we work with a variety of insurance providers. Contact our team to verify your coverage.
Yes, we provide secure online consultations with experienced specialists.
Our care coordinators help match you with the most suitable specialist.
Absolutely. Your medical information is protected according to healthcare privacy standards.
Look at six things: accreditation (JCI or NABH), specialty depth, doctor credentials and experience, procedure-specific success rates, international patient support, and technology. DivinHeal's AI-driven matching evaluates every hospital in our accredited partner network on these dimensions and shortlists the best-fit options for your condition, budget, and country.
JCI (Joint Commission International) is the US-based global gold standard for hospital quality, recognised worldwide. NABH is India's national accreditation — accredited by ISQua, the same body that accredits JCI. Both signal independently verified safety and quality. Most of India's leading hospitals hold both.
Yes. All three welcome international patients through structured medical visa programs. India is the most established, treating patients from Africa, the Middle East, and South Asia at 60–80% lower cost. Thailand leads in cosmetic and dental care. The UAE is emerging in oncology and reproductive medicine.
Most patients save 50–80% on treatment costs. Heart bypass costs US $7,000–9,000 in India compared to $70,000–150,000 in the US. IVF costs $3,000–4,500 compared to $12,000–20,000 in the UK. Even after flights, visa, and accommodation, total savings remain 60–70%.
DivinHeal manages your entire non-medical journey: visa invitation letters, medical visa guidance, doctor appointments, teleconsultations, airport pickup, hospital-vetted accommodation for you and your attendant, language interpreters, local transport, cuisine preferences, and post-treatment follow-up — one dedicated coordinator from first enquiry to final follow-up.
You need a valid passport (6+ months validity), a medical visa (M-Visa for India — DivinHeal provides the hospital invitation letter), return flight tickets, recent medical reports and a doctor's referral, current prescription list, and proof of financial means. Any accompanying attendant needs their own passport and MX-Visa.
Still have more questions?
Book a call with our friendly team to learn how DivineHeal simplifies your healthcare journey.